
Shoulder
Frozen Shoulder - Understanding the Condition and Exploring Treatment Options

Time and again, in our practice BodyLab, osteopathy and Physiotherapy | Rehabilitation and Training in Zurich, we see patients with a painful shoulder and additionally restricted mobility. Often taking a wait-and-see approach, patients only visit a doctor after several months, once significant movement restriction has already manifested.
In this blog post, we look at the development and cause of a so-called frozen shoulder (stiff shoulder), with the goal of educating and informing you so an earlier diagnosis may be possible. Furthermore, treatment options are addressed, and we attempt to discuss and evaluate their effectiveness based on various studies.
What is meant by a frozen shoulder?
A frozen shoulder, also known colloquially as painful shoulder stiffness, is a restriction of passive and active mobility of the shoulder that is painful, especially at the beginning of its course.
In general orthopedic literature, 3 stages of the condition are described:
Phase I: An initial inflammatory phase, which is often characterized by severe pain, especially at night
Phase II: A second phase of stiffening in which, gradually, restricted movement develops in addition to the pain. Over time, everyday movements—such as putting on clothes or fastening your seatbelt in the car—usually become more difficult; pulling, often sharp pains mostly occur in the anterior shoulder area
Phase III: A third phase in which normal mobility slowly returns with the help and support of manual mobilization techniques in Physiotherapy, and the pain disappears
Causes of development
Most often, a frozen shoulder develops idiopathically (meaning the reason and cause are unknown in this case). However, studies indicate that diabetes, shoulder trauma (such as rotator cuff injuries, injuries to the long biceps tendon, impingement issues), thyroid diseases, elevated body weight, and cervical spondylosis are associated with a significantly increased risk of developing it [1]. Factors such as occupational and athletic activity seem to have no influence. The influence of psychological issues and stress is discussed in the literature, but is not clearly proven. It is also interesting that many people often develop a second frozen shoulder in the other shoulder after experiencing one.
What happens in the body
The pathophysiology of frozen shoulder remains largely unexplained to this day. Studies show that capsular inflammation is characterized on the one hand by synovitis, and on the other hand by capsular fibrosis. Cytokines and increased immune system activity appear to be precursors to subsequent fibrosis of the shoulder joint, which is caused by increased activity of fibroblasts.
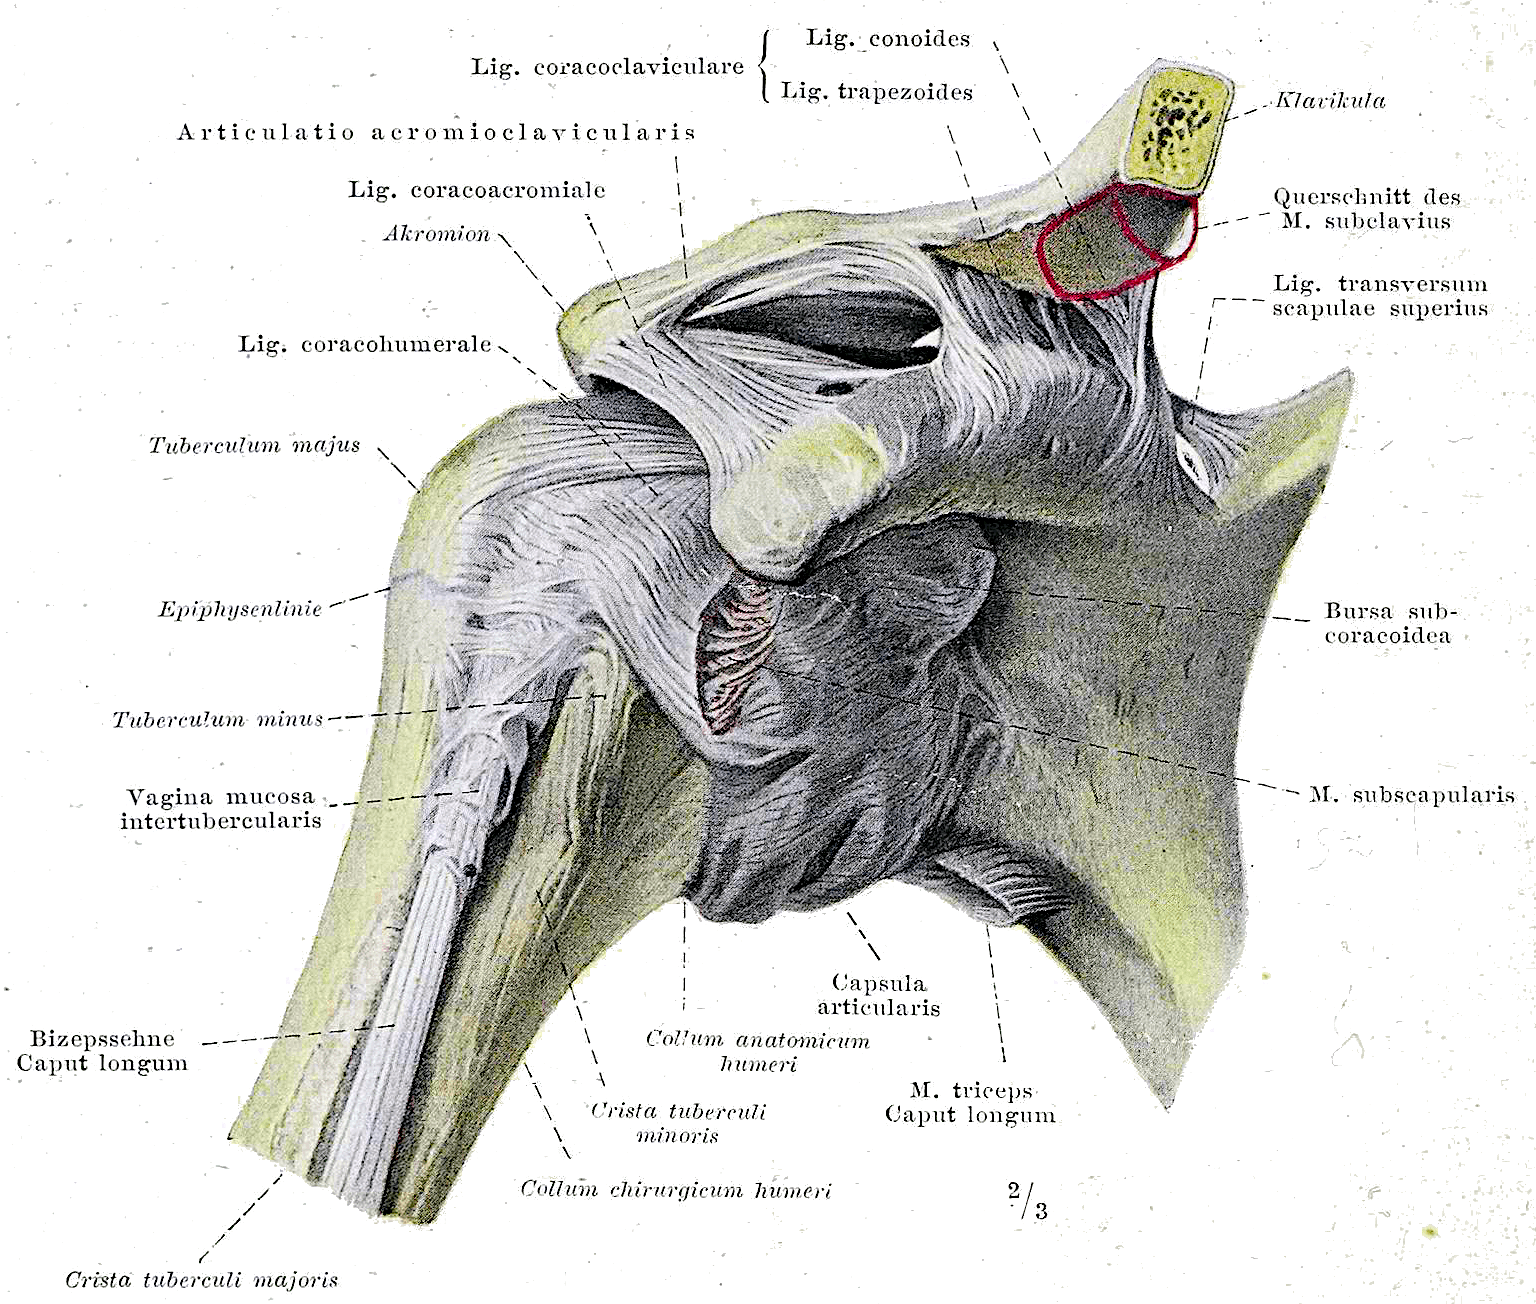
Braus, Hermann, Braus 1921 148, marked as public domain, details on Wikimedia Commons
Recognizing the early stages of a frozen shoulder
Many patients do not recognize the early stages of a frozen shoulder and only consult a doctor late. This is because you often do not consciously notice the shoulder's complex, automatic movement yourself, but instead think about how and where your hand is moving. Initial compensatory movements are often noticed too late. The consequences are advanced fibrotic processes and therefore very frequently a protracted course of therapy. If you feel burning or pulling pain in your shoulder, which initially often occurs at night, you shouldn't wait too long—have your symptoms checked out by a specialist.
The shoulder joint is very complex. The joint must master the balancing act between good mobility and simultaneous stability. Even the smallest changes or excessive strain can lead to problems in the shoulder joint.
The diversity of secondary symptoms is large, and making a diagnosis is often complex; as mentioned, you should leave it to a professional.
Effective forms of therapy
Several studies show high short-term effectiveness of a cortisone injection for pain relief and reducing inflammation, especially during the inflammatory phase [4,7]. From our perspective, particularly for people who are already experiencing their second frozen shoulder, this can make sense early on—but only accompanied by passive manual therapy!
Laser therapy is strongly indicated for early and short-term pain reduction, but it does not improve functionality or range of motion [4,7]
Active exercise therapy, passive physiotherapeutic or osteopathic mobilization are strongly indicated for improving pain and mobility in stages 2 and 3 of a frozen shoulder [4,5]
Electrotherapy, ultrasound, and heat therapy can be used for short-term pain relief. However, long-term studies show little effect [7]
The effectiveness of acupuncture could not be proven [7]
As a last resort, operative arthroscopic capsular release (arthrolysis) has shown to be effective. In this procedure, the inflamed joint lining and capsular adhesions are partially or completely removed. However, this method represents the last resort for relieving symptoms and is usually only applied after months or years of ineffective conservative therapy [6,7]
In summary, a quick diagnosis is helpful. An early medical assessment using MRI is recommended so that an injection can be given if necessary, curbing the inflammatory phase. Conservative therapy should begin promptly once the first phase concludes or nears its end. Active movement therapy and learning specific home exercises are essential for your continued progress. Nevertheless, the most important factor is your perseverance. Despite intensive conservative therapy, the process can take several months or even years.
So, if you feel similar symptoms, don't take it lightly! Get in touch with us or your doctor.
Whenever you need us, we're here for you!
Your BodyLab team, by your side until your shoulder moves freely again
Osteopathy and Physiotherapy | Rehabilitation and Training
Zurich Altstetten
You can find more on this on our frozen shoulder page.
References
[1] Case control study of risk factors for frozen shoulder in China.
Li W, Lu N, Xu H, Wang H, Huang J.
Int J Rheum Dis. 2015 Jun;18(5):508-13. doi: 10.1111/1756-185X.12246. Epub 2014 Jan 18.
[2] Primary frozen shoulder: brief review of pathology and imaging abnormalities
Kazuya Tamai, Miwa Akutsu, and Yuichiro Yano.
J Orthop Sci. 2014; 19(1): 1–5. Published online 2013 Dec 4. doi: 10.1007/s00776-013-0495-x
[3] The pathology of frozen shoulder.
Hand GC, Athanasou NA, Matthews T, Carr AJ.
J Bone Joint Surg Br. 2007 Jul;89(7):928-32.
Jain TK, Sharma NK.
J Back Musculoskelet Rehabil. 2014;27(3):247-73. doi: 10.3233/BMR-130443.
Yang JL, Chang CW, Chen SY, Wang SF, Lin JJ.
Phys Ther. 2007 Oct;87(10):1307-15. Epub 2007 Aug 7.
Smith CD, Hamer P, Bunker TD.
Ann R Coll Surg Engl. 2014 Jan;96(1):55-60. doi: 10.1308/003588414X13824511650452.
[7] Frozen shoulder: the effectiveness of conservative and surgical interventions–systematic review.
Favejee MM1, Huisstede BM, Koes BW.
Br J Sports Med. 2011 Jan;45(1):49-56. doi: 10.1136/bjsm.2010.071431. Epub 2010 Jul 20.


